
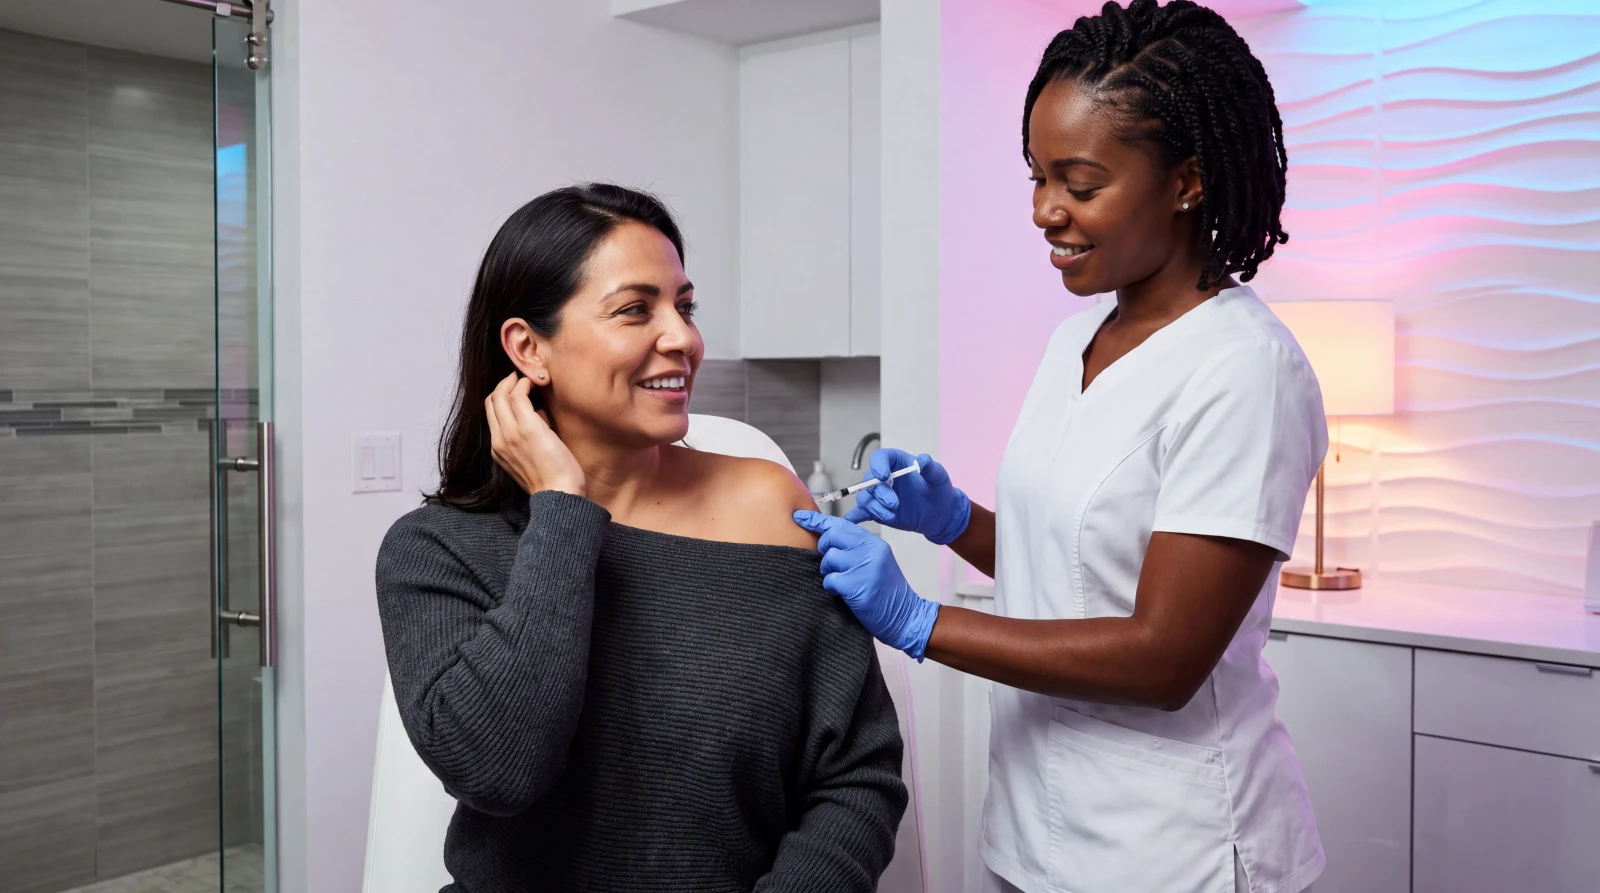
Lipotropic injections Miami clinics offer are sold under a lot of names — the MIC shot, the B12 shot, the skinny shot — and the marketing around them ranges from reasonable to absurd. This article takes the reasonable position, which is also the accurate one: a lipotropic injection is a useful nutritional adjunct with a specific job, and it is not a fat-loss drug.
That is a less exciting claim than the one on most clinic websites. It also happens to be the version that tells you whether it will do anything for you, which is the question you actually came with.
Lipotropic Injections Miami: What Is Actually in the Shot
The standard formulation is MIC + B12, four ingredients with distinct roles.
Methionine — an essential amino acid and the body’s primary methyl donor once converted to S-adenosylmethionine. It participates in the synthesis of phosphatidylcholine, which is required for the liver to package and export triglycerides. Methionine restriction in animal models causes hepatic fat accumulation, which is where the “lipotropic” label originates.
Inositol — a carbocyclic sugar involved in insulin signal transduction and cell membrane structure. The best clinical evidence for inositol is in polycystic ovary syndrome, where myo-inositol supplementation has been shown to improve insulin sensitivity and ovulatory function (1). That is a real, specific finding rather than a general metabolic claim.
Choline — an essential nutrient, and the one with the clearest mechanism here. Choline is required for phosphatidylcholine synthesis and therefore for VLDL export of fat from the liver. Dietary choline deficiency produces hepatic steatosis in humans, and it resolves on repletion (2). Most adults consume less than the recommended intake.
Vitamin B12 — cobalamin, a cofactor in methionine regeneration and in fatty acid metabolism. Deficiency causes fatigue, cognitive fog, and in prolonged cases neurological damage. Given by injection it bypasses gastric and ileal absorption entirely, which matters more than it sounds.
Put together, three methyl-donor and lipid-export nutrients plus a vitamin whose deficiency is common and whose repletion is fast.

What Lipotropic Injections Realistically Deliver
Here is the honest ledger.
Well supported: correction of B12 deficiency and its symptoms. This one is not in dispute, and in a genuinely deficient person the change in energy over two or three weeks is often striking.
Mechanistically sound, clinically modest: choline’s role in hepatic fat export. Choline deficiency causes liver fat accumulation and repletion reverses it — but that is a statement about deficiency, not about accelerating fat loss in someone already replete.
Supported in a specific population: inositol in PCOS-related insulin resistance.
Not supported: MIC injections causing meaningful weight loss on their own. There is no strong controlled trial evidence for it, and we are not going to imply otherwise. Any weight change on a lipotropic protocol is coming from the calorie deficit and the training that accompanied it.
So why give them at all? Because a meaningful share of the people asking are, in fact, depleted — and the shot is a fast, cheap, low-risk way to fix that while the actual weight loss work goes on around it.
Who Genuinely Benefits
The groups where we see a real difference:
- Anyone on a GLP-1. Semaglutide, tirzepatide and retatrutide reduce food intake substantially, and micronutrient intake falls along with calories. Patients eating a third less than they were six months ago are a legitimately at-risk group.
- Long-term metformin users. Metformin impairs B12 absorption, and the effect is dose- and duration-dependent — a well-replicated finding, not a fringe concern (3).
- Vegetarians and vegans. B12 occurs almost exclusively in animal foods. This is the most predictable deficiency in medicine.
- Adults over 60, where reduced gastric acid impairs release of B12 from food protein.
- Anyone on long-term proton pump inhibitors or H2 blockers, for the same reason.
- Post-bariatric patients, where absorptive anatomy has changed permanently.
If you are in none of those groups, eat animal protein regularly and have a normal B12 with normal methylmalonic acid, expect the effect to be modest. That is not a reason not to have it. It is a reason to have accurate expectations about what you are buying.

Where It Fits in a Weight Loss Program
The useful way to think about a lipotropic injection is as one supporting element in a plan whose main drivers are elsewhere.
| Element | Contribution to fat loss |
|---|---|
| Calorie deficit | The mechanism. Everything else modifies it. |
| Protein intake and resistance training | Determines how much of the loss is fat rather than muscle |
| GLP-1 medication, where indicated | Makes the deficit sustainable by reducing appetite |
| Sleep and stress management | Affects adherence, appetite regulation and recovery |
| Lipotropic injection | Supports energy and micronutrient status so the above stays possible |
That last row is genuinely worth something. The most common reason a weight loss plan collapses is not a metabolic failure — it is that the patient is exhausted, training drops off, and adherence follows. Correcting a depletion that is contributing to that fatigue is a reasonable intervention, and it costs very little.
It is also why we most often use these alongside a medical weight loss program rather than instead of one. The muscle-preservation side of that equation is covered in protecting lean mass on a GLP-1, which is the higher-priority problem for most people on these medications.
Protocol, Timeline and Cost Structure
Cadence. Weekly is standard, occasionally twice weekly for the first few weeks in someone clearly depleted. The B12 portion is water-soluble and cleared over days, so the schedule is regular rather than occasional.
Route. Intramuscular, usually deltoid or gluteal, with a small-gauge needle. Many patients self-administer at home after one technique session.
Timeline. If low B12 was contributing to fatigue, one to three injections is usually enough to notice. If it was not, the effect is subtle and you should be told that up front.
Testing. Serum B12 alone is an imperfect marker and can read normal in functional deficiency, so it is worth pairing it with methylmalonic acid or homocysteine. Test before starting so you have a baseline, and re-check at three months.
Cost. Lipotropic injections are inexpensive relative to almost everything else in this category, which is part of why they are so heavily marketed. Ask whether you are being quoted per injection or per package, and whether the initial lab work is included.

Safety and Who Should Skip It
The components are nutrients and the safety profile at these doses is favourable. B12 has no established upper toxic limit and excess is excreted. The most common complaints are transient stinging at the injection site and a brief warm flush.
Situations that need a conversation first: pregnancy and breastfeeding, known allergy to any component, significant renal impairment, and Leber’s hereditary optic neuropathy, where cyanocobalamin specifically is avoided. And anyone with unexplained fatigue should have it investigated rather than injected — fatigue has a long differential, and thyroid disease, anaemia, sleep apnoea and depression are all more common than isolated B12 deficiency.
The Bottom Line
A lipotropic injection is a good, cheap, low-risk adjunct that reliably fixes one specific thing and modestly supports a few others. Used inside a real weight loss program in someone who is actually depleted, it earns its place. Sold as a fat-loss treatment on its own, it does not.
Our approach is on the lipotropic injections page, and the programs it usually sits inside are under medical weight loss. If you are weighing the bigger levers first, semaglutide cost covers what GLP-1 therapy actually runs.
Not sure whether you are depleted or just tired? Start with the lab work. Book a consult with our Miami team.
Medical disclaimer: This article is for educational purposes only and is not a substitute for professional medical advice, diagnosis, or treatment. Lipotropic injections are compounded preparations and are not FDA-approved products for weight loss. Consult a qualified clinician before starting any new treatment.
Sources
- Unfer V, Facchinetti F, Orrù B, et al. Myo-inositol effects in women with PCOS: a meta-analysis of randomized controlled trials. Endocrine Connections. 2017;6(8):647–658.
- Zeisel SH, da Costa KA. Choline: an essential nutrient for public health. Nutrition Reviews. 2009;67(11):615–623.
- de Jager J, Kooy A, Lehert P, et al. Long term treatment with metformin in patients with type 2 diabetes and risk of vitamin B-12 deficiency: randomised placebo controlled trial. BMJ. 2010;340:c2181.
- Green R, Allen LH, Bjørke-Monsen AL, et al. Vitamin B12 deficiency. Nature Reviews Disease Primers. 2017;3:17040.
Frequently Asked Questions
Do lipotropic injections actually cause weight loss on their own?
No, and any clinic telling you otherwise is overselling it. There are no strong controlled trials showing MIC plus B12 produces meaningful weight loss as a standalone intervention. What the ingredients do is support pathways involved in fat metabolism and methylation, and correct a deficiency that causes fatigue. Weight loss comes from the calorie deficit, the protein intake, the resistance training and, where indicated, the medication — the shot supports that work rather than replacing it.
Who gets the most out of a lipotropic injection?
People who were actually depleted. That includes anyone on a GLP-1 whose food intake has dropped sharply, long-term metformin users (metformin reduces B12 absorption over time), vegetarians and vegans, people over 60, anyone on long-term acid-suppressing medication, and post-bariatric patients. In those groups the change in energy is frequently obvious. In someone with normal B12 and a good diet, the effect is understandably smaller.
How often do you get lipotropic injections?
Weekly is the standard cadence, sometimes twice weekly during an initial period. B12 given by injection bypasses the absorption problem entirely, and the water-soluble portion is cleared over days rather than stored indefinitely, which is why the schedule is regular rather than occasional. Many patients self-administer at home after being shown the technique.
How soon will I notice anything?
If low B12 was contributing to your fatigue, most people notice a change within one to three weekly injections. If your B12 was already normal, expect the effect to be subtle. Nothing about this shot should produce a dramatic change in the first week, and a clinic promising one is describing a marketing claim rather than a pharmacological one.
Are lipotropic injections safe?
The components have a favourable safety profile at the doses used. B12 is water-soluble with no established toxic level, and MIC components are nutrients found in food. The most common complaints are transient stinging at the injection site and a brief flush. They are not appropriate in pregnancy without specific guidance, in anyone with a known allergy to a component, or in people with certain kidney conditions, and B12 status should be checked rather than assumed.
Do I need a blood test first?
You should have one. Serum B12 plus methylmalonic acid or homocysteine gives a far more accurate picture than serum B12 alone, which can read normal in functional deficiency. Testing first also gives you a baseline to compare against, which is the only way to know whether the injections are doing anything for you specifically rather than in general.
More in weight loss
Men's Body Fat Percentage Chart by Age (Better Than BMI)
Body fat percentage chart for men by age, why it beats BMI, normal-weight obesity, visceral fat, and protecting muscle on GLP-1 therapy.
weight lossWomen's Body Fat Percentage Chart by Age (Better Than BMI)
Body fat percentage chart for women by age, why it beats BMI, normal-weight obesity, and protecting muscle on GLP-1 therapy.
weight lossGLP-1 Muscle Loss: Protect Lean Mass on Semaglutide
GLP-1 muscle loss is real — a meaningful share of weight lost on semaglutide or tirzepatide can be muscle. Here's why it matters and how to protect lean mass.
⚕ Medical Disclaimer
The information on this page is for educational purposes only and does not constitute medical advice, diagnosis, or treatment. All treatments at Rewind Anti-Aging of Miami are performed under the supervision of licensed medical professionals. Individual results may vary. Consult your physician before beginning any new treatment protocol.
Meet our clinical team →Not sure which treatment is right for you?
Take our free 2-minute assessment and get a personalized recommendation.
Areas We Serve in Miami & South Florida
Our clinic at 24 NW 29th Street is in Wynwood & Midtown, minutes from Edgewater and Brickell. We also care for patients across Coral Gables, Aventura, Key Biscayne, and Doral — plus the entire state of Florida via telehealth.
Take the Next Step
Our team at Rewind Anti-Aging in Miami is here to help you determine if medical weight loss is right for your goals.